Patients ask me this constantly before surgery: "Doctor, what will my life look like in the weeks after?" So instead of general timelines, here's what I tell them in clinic.
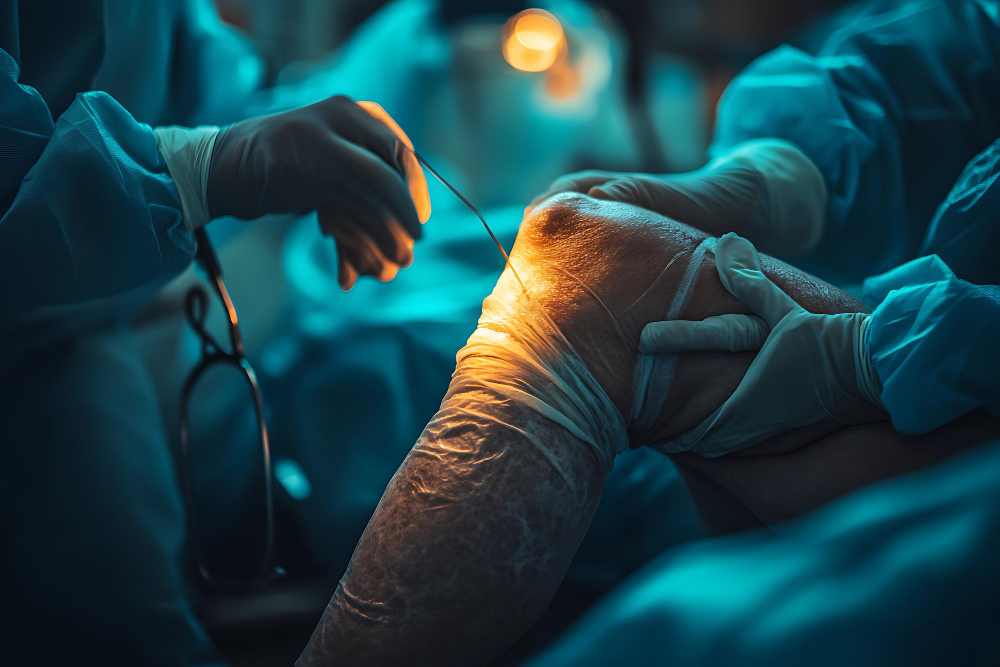
The first 24 hours surprise most people — we get patients standing, sometimes taking a few steps, on the very same day as surgery. It's not about rushing; early movement is what keeps the new joint from stiffening up.
By the end of week one, swelling is still visible and some discomfort is expected — that's normal healing, not a setback. Physiotherapy starts almost right away, even if it's just gentle bending exercises in bed.
Somewhere between weeks two and four, I usually see patients graduate from a walker to a cane. This is also when they start managing small tasks around the house again — making tea, walking to the gate.
Weeks four through eight are where confidence really builds. Most patients come off strong painkillers, and if their work is desk-based, they're often cleared to drive and return to the office.
By three months, the joint starts to feel like "theirs" again — climbing stairs without thinking about it, walking longer distances, maybe even getting back into the pool.
Beyond six months, especially with robotic-assisted precision guiding the initial surgery, I see patients return to nearly all their regular activities, sometimes surprising themselves with how far they've come.
No two recoveries look identical — age, prior fitness, and how closely someone follows their physiotherapy plan all shape the outcome. If you're weighing knee replacement, let's sit down and map out what your specific recovery might look like.
"But Won't I Be Stuck in Bed for Months?" — Knee Replacement Myths I Hear Every Week
Running an orthopedic clinic in Panchkula for over a decade, I've heard every fear in the book about knee replacement. Let's clear a few up.
"It's only for old people."
I've operated on patients in their 40s with severe sports-related arthritis. Age matters less than joint condition — modern implants are built to handle active lives, not just slow ones.
"The pain and recovery will be unbearable."
This one's outdated. Between better pain-management protocols and robotic-assisted techniques, most of my patients are up and walking within a day. It's genuinely a different experience than what surgery looked like fifteen years ago.
"I'll never sit cross-legged again."
Partially true, partially myth. Deep bending depends on the implant design — some newer implants are specifically engineered with Indian sitting and prayer habits in mind. Worth a direct conversation with your surgeon rather than assuming the worst.
"Better to wait as long as possible."
Actually the opposite. Waiting too long often means more muscle wasting and bone loss, which makes the surgery — and recovery — harder, not easier.
"All knee replacements are basically the same procedure."
Not even close. Traditional, minimally invasive, and robotic-assisted approaches each come with different recovery profiles. The "right" one depends entirely on your joint, not a one-size-fits-all protocol.
Fear usually comes from outdated information. If something you've heard is holding you back, bring it to your next consultation — I'd rather address it directly than have it delay your treatment.
Sprain or ACL Tear? A Quick Field Guide From the Clinic
Every cricket and badminton season, I see a wave of knee injuries walk into my OPD. Most patients can't tell whether it's a minor sprain or something more serious — here's how I differentiate the two.
A sprain is essentially a ligament being stretched or slightly torn, usually from an awkward twist or landing. It hurts, it swells a little, but it typically settles down within a couple of weeks with rest, ice, and some physiotherapy.
An ACL tear is a different story. The anterior cruciate ligament keeps your knee stable during sudden stops or direction changes — exactly the kind of movement common in football, basketball, or badminton. When it tears, patients often describe:
- Hearing or feeling a distinct "pop" at the moment of injury
- Swelling that comes on fast, sometimes within the hour
- A sense that the knee might "give way" underneath them
- Trouble putting full weight on the leg afterward
Here's my rule of thumb for patients: if there's a popping sensation, rapid swelling, or the knee feels unstable when you try to walk, don't wait it out — come in for an evaluation. An MRI and clinical exam can usually confirm what's going on, and catching it early keeps your treatment options open, from physiotherapy to arthroscopic reconstruction if needed.
Left unaddressed, ACL injuries tend to cause ongoing instability and can speed up arthritis in that joint down the line. It's a small appointment now versus a much bigger problem later.
Is Your Hip Pain Just "Getting Older," or Something More?
I hear this a lot in clinic: "Doctor, it's probably just age." Sometimes that's true. Often, it isn't — and there's a meaningful difference between normal wear and a joint that needs intervention.
Chronic hip pain in patients over 50 usually traces back to osteoarthritis, avascular necrosis, old fractures, or years of cumulative joint stress.
A few signals tell me it's time to talk seriously about joint replacement, rather than continue managing symptoms:
- Pain that won't let you sleep, or that's present even sitting still
- Stiffness bad enough to interfere with walking or standing up from a chair
- Physiotherapy and medication no longer making a real difference
- A visible limp, or leaning on a cane or walker to get around
- Struggling with basics — putting on shoes, getting into a car
I want to be clear: not every hip pain case needs surgery. Depending on severity, we often start with weight management, targeted physiotherapy, or medication first. Surgery becomes the right conversation once those options stop giving meaningful relief.
When it does come to that point, modern hip replacement isn't what it used to be. Minimally invasive and robotic-assisted techniques mean smaller incisions, less blood loss, and — in many of my patients — walking again within a day of the procedure.
If your hip pain is starting to shape your daily decisions — what you can and can't do — it's worth getting evaluated rather than assuming it's just something to live with.
"Will I Ever Play Sports Again?" — An Honest Answer About Life After Knee Replacement
This is probably the single most common question I get before surgery, and patients deserve a straight answer rather than vague reassurance.
For everyday movement — walking, stairs, getting around the house — most patients end up better off than they were in the months before surgery, when pain was likely limiting them already.
Low-impact activities tend to bounce back well. Walking, swimming, cycling, golf — I typically see patients return to these within a few months as strength rebuilds.
Trekking is often possible too, particularly on manageable terrain, though I always tell patients to build up gradually rather than jumping straight back into a difficult trail.
Sitting cross-legged is the question I get asked most, and the honest answer is: it depends. Implant type and how your body heals both play a role. Some newer implant designs support deeper flexion than older models — this is genuinely worth discussing before surgery if it matters to your daily or religious practices.
What I generally discourage is a return to high-impact sport — competitive badminton, football, anything involving running and sudden pivots. The forces involved put unnecessary stress on an artificial joint.
The honest summary: recovery isn't one-size-fits-all. Implant choice, surgical precision, and how seriously you take rehab all shape the outcome. That's exactly why I have this conversation with every patient before, not after, surgery.
Robotic vs. Traditional Knee Replacement: What Changes for You, the Patient
Patients often ask if "robotic" just means a fancier price tag. It doesn't — here's what genuinely changes for someone lying on the operating table.
In traditional surgery, implant placement depends heavily on the surgeon's hands-on judgment and experience. With robotic assistance, real-time imaging and computer guidance help position the implant with a level of precision matched to your individual joint anatomy — not a generic template.
Because the cuts are more controlled, robotic systems also tend to preserve more of the healthy bone and soft tissue around the joint compared to conventional methods.
There's also a consistency factor. The system helps with alignment and balancing the joint, which reduces the variability that can otherwise creep in from case to case.
In my own experience, patients undergoing robotic-assisted procedures often have a smoother early recovery — partly from more accurate positioning, partly from less soft-tissue disruption. That said, overall health and commitment to physiotherapy still matter enormously.
To be clear: robotic assistance is a tool, not a replacement for surgical judgment. I still make every clinical decision — the system simply helps execute the plan with greater precision.
Both approaches can deliver excellent results in experienced hands. Robotic guidance simply adds an extra layer of accuracy, which matters most in complex cases or where precise alignment is critical.
Inside the OR: What Robotic-Assisted Surgery Actually Looks Like
Patients are often curious — sometimes nervous — about what "robotic surgery" really means in practice. Let me walk you through it.
Before we ever enter the operating room, we take detailed scans of your joint to build a 3D model. This gives us a precise map of your unique anatomy, rather than relying on standard measurements.
Using that model, I plan the surgery in advance — exactly where the bone cuts will go, how the implant will sit, all mapped out before the first incision.
In the OR itself, the robotic arm doesn't operate on its own — I'm the one performing the surgery, with the system acting as a guide that keeps every movement within the boundaries we planned.
As surgery progresses, the system continuously feeds back data on alignment, ligament tension, and bone position, letting me fine-tune adjustments in real time for the best possible joint balance.
That precision carries through to implant placement — positioned to support natural movement and reduce unnecessary stress on the surrounding tissue.
Once everything checks out, we close the incision, and most patients begin light movement and physiotherapy within just a few hours.
At the end of the day, the robot is an instrument — a very precise one — but the surgical judgment, the planning, and the decisions throughout the procedure still come from years of clinical training.
Smaller Cuts, Faster Comebacks: The Case for Minimally Invasive Surgery
If there's one shift that's genuinely changed recovery for my patients over the years, it's the move toward minimally invasive technique.
Older surgical approaches often required larger incisions and more cutting through muscle to reach the joint. Minimally invasive methods use smaller incisions and purpose-built instruments, which means far less disruption to the tissue around the joint.
That translates directly into less blood loss during the procedure itself.
Patients also tend to report noticeably less pain in the days that follow — which means less reliance on strong painkillers.
Mobility comes faster too. Where traditional surgery often meant longer bed rest, many of my minimally invasive patients are standing and moving within hours.
Shorter hospital stays naturally follow, letting patients continue recovering in the comfort of their own home sooner rather than later.
There's also a lower risk of certain complications, like infection, simply because there's less exposed tissue and a smaller surgical footprint overall.
That said, minimally invasive isn't automatically right for every case — joint complexity and individual anatomy still guide that decision. It's something we assess together during your evaluation.
Simple Habits That Keep Knees Healthy Longer
You don't need a gym membership to protect your knees — some of the most effective habits are the simplest ones. Here's what I recommend to patients looking to stay ahead of joint problems.
A daily walk does more than people realize — it keeps the joint lubricated and strengthens the surrounding muscles without overloading the knee itself.
Swimming and water aerobics are particularly kind to the joints, since the water takes the body's weight off the knees while still building strength.
Cycling — indoor or outdoor — is excellent for building up the quadriceps and hamstrings, the muscles that essentially act as shock absorbers for the knee.
Basic strength work matters too. Controlled squats, leg presses, and step-ups build muscle around the joint, which takes pressure off the knee itself over time.
Don't skip stretching — loosening the hamstrings, quads, and calves helps preserve range of motion and keeps stiffness from creeping in.
And simple balance drills, like standing on one leg, reduce fall risk — which matters more than people think, since falls are a major cause of sudden knee injury in older adults.
A couple of cautions: skip high-impact activity like running on concrete if you're already having joint pain, always warm up first, and stop immediately if you feel persistent pain or instability during movement.
None of this needs to be intense. Consistency beats intensity, every time, when it comes to protecting your joints.
The Weekend Warrior's Guide to Avoiding Injury
I see a predictable pattern every Monday morning — patients who played an intense match over the weekend and woke up with a knee or ankle that isn't cooperating. Here's how to avoid becoming one of them.
Start with a proper warm-up — light jogging, leg swings, joint mobility drills. Skipping this step is one of the most common (and avoidable) causes of injury I see.
If you're only active once a week, your body isn't conditioned for the sudden demand. Even short strength routines during the week make a real difference in injury resistance.
Footwear matters more than people give it credit for — the right shoe for your sport absorbs shock that would otherwise land directly on your knees and ankles.
Ease into higher intensity rather than jumping straight back in, especially after a break — your muscles and joints need time to adapt.
Technique also plays a bigger role than most weekend players assume. Poor form during running, jumping, or lifting is a fast track to injury — a session or two with a coach can go a long way.
Pay attention to your body's warning signs. Persistent soreness or a knee that feels like it might "give way" isn't something to push through — it's a signal to back off.
And don't underestimate recovery itself — proper rest, hydration, and sleep are as much a part of injury prevention as the activity itself.
If an injury does happen — sudden swelling, instability, difficulty bearing weight — get it evaluated quickly. Early assessment often means the difference between a short recovery and a long one.
Eating for Stronger Bones: What I Tell My Patients
Joint health isn't only about movement — what's on your plate plays a real role too. Here's the nutrition guidance I regularly give patients focused on long-term bone and joint health.
Calcium is the obvious starting point — dairy like milk, yogurt, and paneer are reliable sources, along with leafy greens such as spinach and methi.
Vitamin D works alongside calcium, helping your body actually absorb it. Sunlight is the most natural source, though egg yolks, fortified milk, and fatty fish help too.
Protein often gets overlooked in joint health conversations, but the muscles supporting your joints need it to stay strong and absorb everyday impact. Lentils, dairy, eggs, and lean meats are good everyday sources.
Omega-3 fatty acids, found in fish like salmon and mackerel, along with walnuts and flaxseeds, carry anti-inflammatory properties that can ease joint stiffness over time.
On the flip side, I'd suggest going easy on sugar, heavily processed foods, and excess salt — all of which can quietly contribute to inflammation.
Weight matters more than most people expect — every extra kilogram adds real, compounding stress to weight-bearing joints like the knees and hips. A balanced diet that supports a healthy weight is one of the most underrated things you can do for your joints.
And don't overlook hydration — cartilage is largely water, and staying hydrated supports how well your joints move and cushion impact.
None of this requires a strict diet overhaul — small, consistent choices add up considerably over the years.
Picking the Right Orthopedic Surgeon: Questions Worth Asking Before You Commit
Choosing a surgeon is a bigger decision than most people treat it as. Here's what I'd encourage anyone in Panchkula or Chandigarh to ask before committing to a procedure.
Start with experience — how many similar procedures has the surgeon actually performed, and specifically with your condition, whether that's an ACL reconstruction or a full joint replacement?
Ask what surgical techniques are actually on offer. Does the surgeon provide minimally invasive or robotic-assisted options, and how do they decide which approach fits your specific case?
Push for honesty on outcomes and risk — a surgeon worth trusting will walk you through realistic scenarios, not just the best-case story.
Ask what recovery actually looks like — the physiotherapy plan, the expected milestones, and what support is available while you heal.
Facility quality matters too — the technology in the operating room and the standard of post-operative care both influence how smoothly things go.
A confident surgeon shouldn't be uneasy about you seeking a second opinion — in fact, welcoming that is usually a good sign.
Ask about follow-up access. How reachable is the surgeon if something feels off during recovery?
And finally, talk to other patients if you can. Reviews and word-of-mouth experiences often reveal more about communication style and real outcomes than a website ever will.
Take your time with these questions — the right fit matters as much as the procedure itself.

Dr. Anand Jindal

Director

Ortho, Joint Replacement & Sports Medicine